If one of you carries a balanced translocation, you have already been given an explanation for the miscarriages, and it is usually the first explanation that has made sense. The natural next question is whether embryo testing can stop it happening again. The honest answer is more nuanced than most clinic pages admit: PGT-SR can reduce the chance of another miscarriage and shorten the time to a live birth, but it does not clearly increase the chance that you eventually have a baby, because most translocation carriers get there anyway. Here is what that means for your decision.
What a Balanced Translocation Is
A translocation is a rearrangement in which segments of two chromosomes have swapped places. In a balanced translocation, no genetic material has been gained or lost, it has simply been repositioned. The person carrying it is entirely healthy, usually with no symptoms at all, and most carriers only discover it after investigation for repeated miscarriage.
There are two main types.
Reciprocal translocations, where segments are exchanged between two non-homologous chromosomes.
Robertsonian translocations, where two acrocentric chromosomes fuse, most commonly involving chromosomes 13, 14, 15, 21 and 22.
The distinction matters practically, because reciprocal translocation carriers tend to experience more pregnancy losses than Robertsonian carriers.
Why It Causes Miscarriage
The problem arises at meiosis, when eggs or sperm are formed. The rearranged chromosomes have to pair and separate, and because of the altered structure, that separation frequently goes wrong.
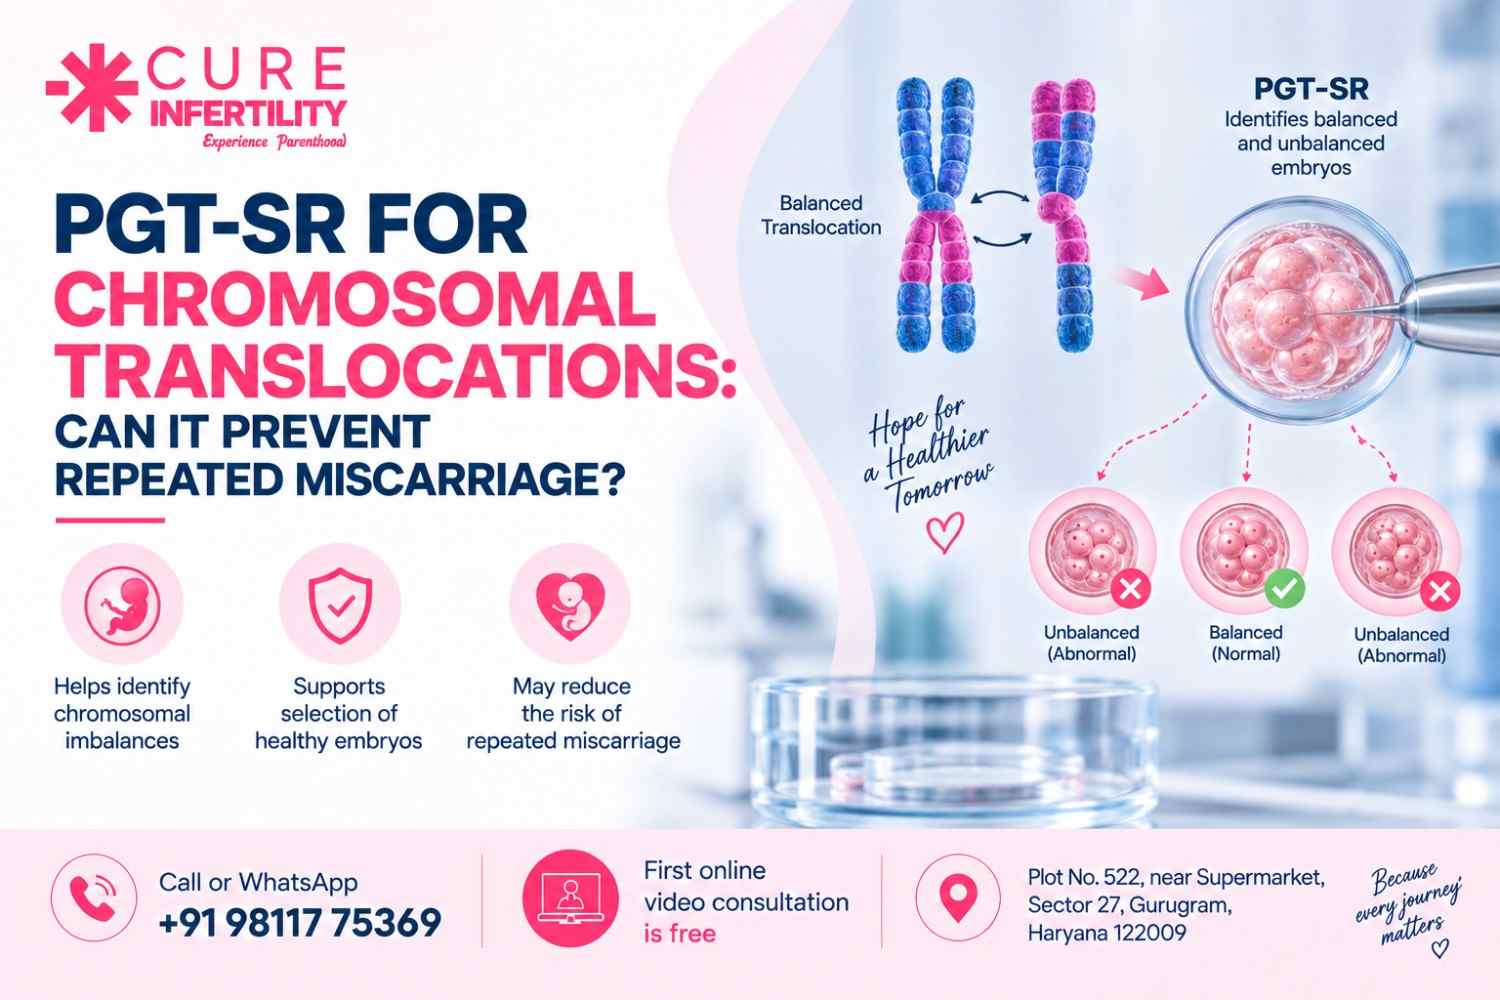
The result is that a carrier produces a mixture of gametes. Some are chromosomally normal. Some carry the same balanced rearrangement, and an embryo from these is healthy, like the carrier parent. And a substantial proportion are unbalanced, carrying extra or missing genetic material.
Unbalanced embryos usually fail to implant or miscarry early. Occasionally one continues, which is the situation that leads to a child with congenital abnormalities, though in carrier couples this outcome is uncommon.
This is why the miscarriages are typically early and repeated. It is not a problem with the uterus or with hormones. It is arithmetic at the point of gamete formation.
How Common Is This?
Balanced parental translocations account for roughly 2 to 5 percent of recurrent pregnancy loss cases. That makes it an uncommon but far from rare finding, and an important one, because unlike much of recurrent loss it has a definite, identifiable cause.
Guidelines differ on who should be karyotyped. ESHRE does not recommend routine parental karyotyping in all couples with recurrent loss, advising it after individual risk assessment or when testing of pregnancy tissue shows an unbalanced rearrangement. ASRM has historically taken a broader view. Canadian guidance suggests it may be considered after three or more first trimester losses, or where products of conception show an unbalanced structural abnormality.
The practical consequence is that if you have had repeated losses, ask specifically whether karyotyping is indicated in your case rather than assuming it has been covered.
What PGT-SR Does
Preimplantation Genetic Testing for Structural Rearrangements screens embryos created through IVF to identify which are chromosomally balanced, either normal or carrying the same balanced rearrangement as the parent, and which are unbalanced. Only the balanced ones are transferred.
This is a different test from the other two forms of embryo testing, though they are often confused.
PGT-A screens for whole chromosome number abnormalities in embryos, without reference to family history. PGT-M tests for a specific single-gene disease known to run in the family. PGT-SR is specifically for structural rearrangements such as translocations and inversions, and modern testing platforms usually report chromosome number alongside the rearrangement, so the two overlap in practice.
The Honest Evidence
This is where most articles on this topic overstate the case, so it deserves care.
What PGT-SR does well. It reduces the miscarriage rate per pregnancy, because unbalanced embryos are identified and not transferred. It can shorten the time to a live birth, avoiding the cycle of conceiving, losing, and recovering. Canadian guidance supports considering it for exactly those two reasons in carriers of balanced reciprocal or Robertsonian translocations, though it rates the strength of that recommendation as conditional and the underlying evidence as low quality.
What it does not clearly do. It has not been shown to reliably increase the cumulative chance of eventually having a baby. ESHRE's position is that the limited evidence for preimplantation genetic testing in recurrent pregnancy loss shows no clear benefit, and the quality of that evidence is very low.
The number that explains why. The cumulative live birth rate for translocation carriers without any medical intervention is around 70 percent. Most carrier couples who keep trying naturally do eventually have a healthy child. PGT-SR is therefore not rescuing an impossible situation. It is changing the route.
The risk that is often overstated. The chance of an ongoing pregnancy with an unbalanced translocation, meaning a baby born with a chromosomal abnormality, is low, reported at under 1 percent in carrier couples. Most unbalanced embryos are lost early rather than continuing.
So Is It Worth Doing?
The evidence supports a real but specific benefit: fewer miscarriages along the way, and potentially a faster route. That is not nothing. Anyone who has been through three or four losses understands that avoiding another is worth a great deal in itself, separately from the eventual outcome.
The factors that push toward PGT-SR:
- A high number of previous losses, where the emotional cost of another is the main consideration
- Advancing maternal age, where time genuinely matters and cumulative attempts are limited
- A reciprocal translocation, which carries a higher loss rate than Robertsonian
- Coexisting infertility, where IVF is needed anyway, in which case adding testing is a small step rather than a new undertaking
- A previous pregnancy or child with an unbalanced rearrangement
- A strong personal preference to avoid another loss rather than to keep trying naturally
The factors that push against it:
- Younger maternal age with good ovarian reserve and time available
- A Robertsonian translocation with fewer losses
- No infertility, meaning natural conception happens readily
- Few embryos likely, since testing narrows an already small pool
- Cost and the willingness to undergo IVF when conception itself is not the problem
The genuinely honest framing is that this is a trade-off between two reasonable paths, not a choice between a solution and a failure. Natural conception with prenatal diagnosis is a legitimate route. So is PGT-SR. What is not legitimate is being told PGT-SR is the only way to have a healthy child, because the data does not support that.
What the Process Involves
The cycle follows the standard IVF sequence: stimulation, egg retrieval, then fertilisation by ICSI, which is used because stray sperm on the outside of the egg would contaminate the genetic sample. Embryos are grown to blastocyst, a few cells are biopsied from the outer layer that becomes the placenta, and embryos are frozen while testing is carried out. Transfer happens in a later frozen cycle.
Depending on the specific translocation and the testing platform, a preliminary workup on the carrier's blood may be needed before the cycle, so ask about timelines early rather than assuming the cycle can start immediately.
The Number of Embryos Problem
This is the practical issue that most affects whether PGT-SR delivers for you.
A translocation carrier produces a high proportion of unbalanced gametes, so a large share of embryos will be excluded. Add chromosomal abnormalities unrelated to the translocation, which rise with maternal age, and the pool narrows further. Some embryos return inconclusive results.
The consequence is that egg numbers matter more here than in a standard cycle. Age and ovarian reserve drive the outcome substantially, as covered in our articles on IVF success rates by age and low AMH and pregnancy. Many couples bank embryos across two or more stimulation cycles before testing, and it is reasonable to plan for that from the outset rather than being surprised by it.
It is also possible to complete a cycle and find no transferable embryo. That outcome should be discussed before you start, not after.
Balanced Carrier Embryos
A question that comes up often: should an embryo carrying the same balanced translocation as the parent be transferred?
Generally yes. A balanced carrier is healthy, which the carrier parent demonstrates. The child would face the same reproductive considerations in adulthood, and that is worth discussing, but it is not a health problem in itself. Where enough embryos exist, some couples prefer to transfer a completely normal embryo first, which is a reasonable preference rather than a medical requirement.
Ruling Out Everything Else
Finding a translocation does not mean it is the only thing causing your losses. Roughly a third of losses in carrier couples are attributable to the translocation, with the remainder due to chromosomal abnormalities arising independently, other causes, or unexplained factors.
A complete recurrent loss workup should still cover antiphospholipid antibodies, thyroid function, uterine cavity assessment, and where relevant chronic endometritis. Our articles on hysteroscopy before IVF and tests to consider after repeated IVF failure cover the uterine side of that assessment.
Attributing everything to the translocation and stopping the investigation there is a real and common error.
Genetic Counselling
Every guideline agrees on this point, even where they disagree on PGT. Couples with an abnormal parental karyotype should receive genetic counselling covering the specific rearrangement, the realistic proportion of embryos likely to be unbalanced, the chance of an affected live birth, and all the available options including natural conception with prenatal diagnosis, PGT-SR, donor gametes and adoption.
It is also worth knowing that a balanced translocation is inherited. Siblings and other relatives of the carrier may be carriers themselves, often without knowing, and testing is worth offering to them.
The Honest Summary
A balanced translocation is a definite, identifiable cause of recurrent miscarriage, which itself is worth something after years of unexplained loss. PGT-SR can reduce the miscarriage rate and shorten the path to a live birth. It has not been shown to change whether you eventually have a child, and most carrier couples do.
Which route suits you depends on your age, how many losses you have had, which type of translocation is involved, whether you also have infertility, and how much another loss would cost you. Both paths are defensible. Any centre telling you otherwise is not giving you the full picture.
You can read more on the PGT and IVF treatment pages, and see the full range of treatment options here.
You can book a free consultation with Dr. Rashmi Agrawal at the Sector 27, Gurugram clinic to review your karyotype reports and discuss which route fits your situation, read more about her background and approach, or check the FAQ page.
FAQs
Can PGT-SR prevent miscarriage completely?
No. It reduces the miscarriage rate by avoiding the transfer of unbalanced embryos, but miscarriage can still occur for other reasons, and no testing eliminates the risk entirely.
What is a balanced translocation?
A rearrangement where segments of two chromosomes have swapped places without any genetic material being gained or lost. The carrier is healthy and usually has no symptoms, but can produce unbalanced eggs or sperm.
How common are translocations in recurrent miscarriage?
Balanced parental translocations account for roughly 2 to 5 percent of recurrent pregnancy loss cases.
Can I have a healthy baby naturally with a translocation?
Yes, and most carriers do. The cumulative live birth rate for translocation carriers without medical intervention is around 70 percent, though the path may involve further losses.
Should a balanced carrier embryo be transferred?
Generally yes. A balanced carrier is healthy, as the carrier parent demonstrates, though the child would face the same reproductive considerations in adulthood.
What is the difference between PGT-SR, PGT-A and PGT-M?
PGT-SR is for structural rearrangements such as translocations. PGT-A screens for chromosome number abnormalities regardless of family history. PGT-M tests for a specific inherited single-gene disease.
Who should have parental karyotyping?
Guidelines differ. ESHRE advises it after individual risk assessment or where pregnancy tissue shows an unbalanced rearrangement. Other bodies suggest it after three or more first trimester losses. Ask whether it is indicated in your specific case.
Do my siblings need testing?
Possibly. Balanced translocations are inherited, so relatives may be carriers without knowing. Testing is worth offering, particularly to those planning a family.
References
- Society of Obstetricians and Gynaecologists of Canada. Guideline No. 464: Recurrent Pregnancy Loss. Journal of Obstetrics and Gynaecology Canada. https://www.jogc.com/article/S1701-2163(25)00413-X/abstract
- ESHRE Guideline Group on Recurrent Pregnancy Loss. ESHRE Guideline: Recurrent Pregnancy Loss (Update). European Society of Human Reproduction and Embryology. https://www.eshre.eu/Guidelines-and-Legal/Guidelines/Recurrent-pregnancy-loss
- American Society for Reproductive Medicine Practice Committee. Recurrent Pregnancy Loss: A Committee Opinion. https://www.asrm.org/practice-guidance/practice-committee-documents/recurrent-pregnancy-loss-a-committee-opinion-2026/